
How Hormones Change During the Menstrual Cycle
Four hormones — FSH, estrogen, LH, and progesterone — rise and fall in a coordinated pattern that drives every stage of your cycle, from your period through ovulation and back again. Here’s what each one does, when it peaks, and how they work together.
The Four Key Hormones
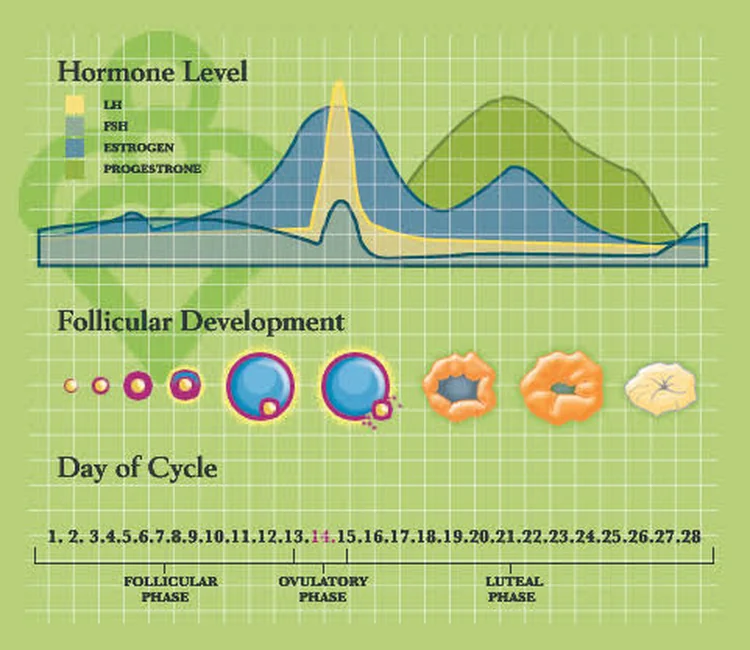
Four hormones drive the cycle: FSH and LH (from the pituitary gland), and estrogen and progesterone (from the ovaries). Each rises and falls at a different point in the cycle, and together they control every phase.
Your menstrual cycle is coordinated by a communication loop between your brain and your ovaries, sometimes called the hypothalamic-pituitary-ovarian (HPO) axis — this axis is the engine behind how hormones change during the menstrual cycle. The hypothalamus releases GnRH in pulses, which signals the pituitary gland to release follicle-stimulating hormone (FSH) and luteinizing hormone (LH). These, in turn, prompt the ovaries to produce estrogen and progesterone. It’s a feedback loop — rising and falling hormone levels signal back to the brain, which adjusts its own signals in response.
What Are Reproductive Hormones?
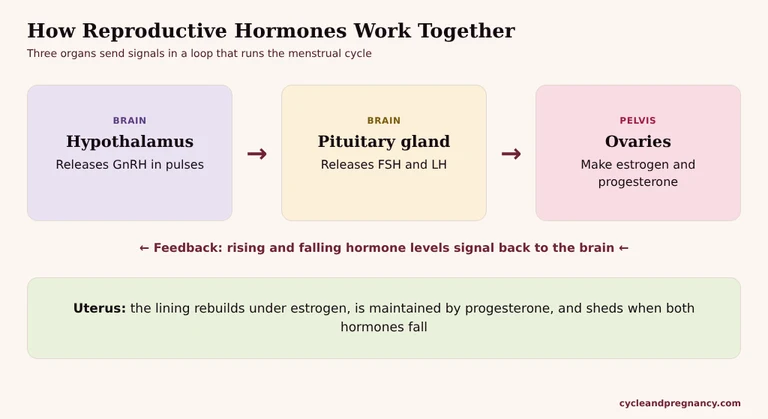
Hormones are chemical messengers made by glands and carried in the blood to tissues, where they change how cells behave. Reproductive hormones are the ones that control the menstrual cycle, ovulation and pregnancy. They are made in three places: the hypothalamus in the brain (GnRH), the pituitary gland (FSH and LH) and the ovaries (estrogen and progesterone). Because they work as a loop, a change in one usually shifts the others.
How Many Hormones Are Involved in the Menstrual Cycle?
Four main hormones are usually described: FSH, LH, estrogen and progesterone. Several others play supporting roles. GnRH starts the chain, and inhibin helps limit FSH once a dominant follicle has formed. Prolactin can stop ovulation when it is too high, thyroid hormones affect cycle regularity, and the ovaries also make small amounts of testosterone. Stress hormones such as cortisol can interfere with the signals from the brain as well.
Hormones During the Menstrual Phase

At the start of your period, estrogen and progesterone are both at their lowest point in the cycle. This drop is actually what triggers menstruation — without it, the uterine lining wouldn’t shed. That same shedding process also releases prostaglandins, which is largely why period cramps tend to be strongest in the first day or two. As bleeding begins, FSH starts rising again, signaling the ovaries to begin developing a new group of follicles for the upcoming cycle.
Hormones During the Follicular Phase

FSH stimulates several follicles in the ovaries to develop, each containing an immature egg. Typically one follicle becomes dominant, and as it grows, it produces increasing amounts of estrogen. Rising estrogen does two things: it signals the uterine lining to rebuild after your period, and it eventually triggers the LH surge that leads to ovulation. Interestingly, developing follicles also release a hormone called inhibin, which helps suppress FSH production once a dominant follicle has been established — this is part of why usually only one egg matures per cycle.
The LH Surge and Ovulation
When estrogen reaches a high enough level, it triggers a sharp surge in luteinizing hormone (LH) from the pituitary gland. This LH surge is what actually causes the dominant follicle to rupture and release its egg — ovulation. The surge typically happens 24 to 36 hours before the egg is released, which is exactly what ovulation predictor kits are designed to detect in urine.
Hormones During the Luteal Phase

After ovulation, the ruptured follicle transforms into a temporary hormone-producing structure called the corpus luteum — Its job is to produce progesterone, which rises through the luteal phase to prepare and maintain the uterine lining in case a fertilized egg needs to implant. Estrogen also has a smaller second rise during this phase, though progesterone is the dominant hormone here. If pregnancy doesn’t occur, the corpus luteum breaks down roughly 14 days after ovulation, and both hormones drop sharply — triggering the next period and restarting the cycle.
How Estrogen and Progesterone Work Together
Estrogen and progesterone don’t just rise and fall independently — they regulate each other and the hormones that control them, which is a big part of how hormones change during the menstrual cycle from phase to phase. Rising estrogen in the follicular phase eventually triggers the LH surge (a rare example of estrogen having a positive feedback effect). Once progesterone rises after ovulation, though, it switches to suppressing LH and FSH production, which is part of why you don’t ovulate twice in one cycle. This back-and-forth signaling is also the basis for how hormonal birth control works, since steady synthetic hormone levels prevent the natural surge needed to trigger ovulation.
Hormone Levels Throughout a 28-Day Cycle
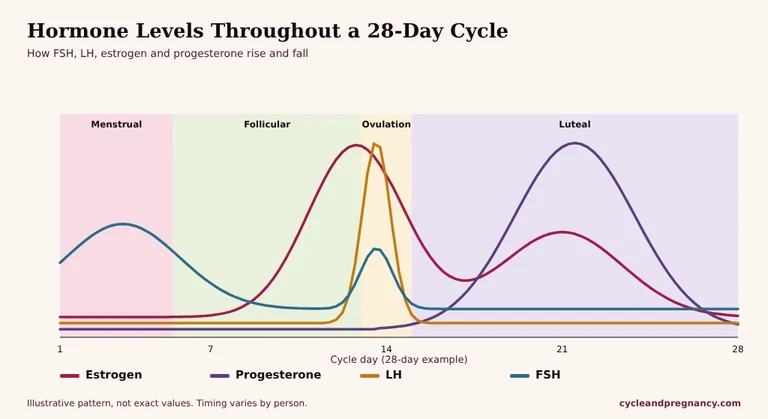
Using a 28-day cycle as a general example (Day 1 = first day of your period):
| Cycle Days | Phase | What’s Happening Hormonally |
|---|---|---|
| Days 1–5 | Menstrual | Estrogen and progesterone at their lowest; FSH begins rising |
| Days 1–13 | Follicular | FSH stimulates follicle growth; estrogen rises steadily |
| ~Day 14 | Ovulation | LH surges sharply, triggering egg release |
| Days 15–28 | Luteal | Progesterone rises, then both hormones drop before the next period |
These day numbers are only an example — actual timing shifts with your individual cycle length, since the follicular phase varies more than the luteal phase does.
Effects of Hormonal Changes on the Body
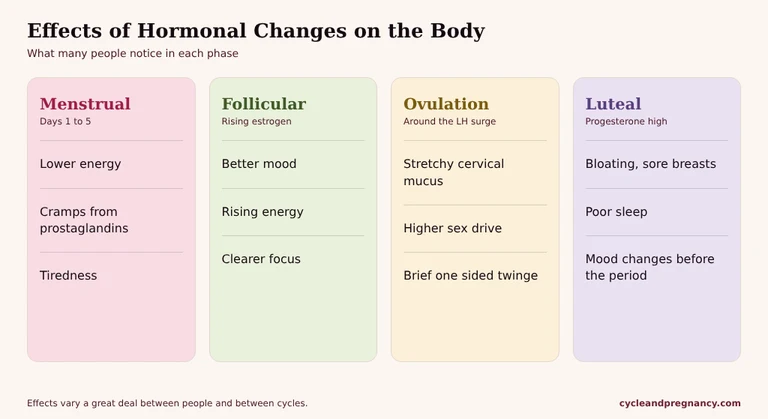
Hormone shifts can be felt, although how much varies a great deal between people and between cycles. Many people notice better mood and energy as estrogen rises in the follicular phase. Around ovulation, some notice clearer, stretchy cervical mucus, a higher sex drive or a brief one-sided twinge (see the signs of ovulation).
After ovulation, progesterone can bring bloating, sore breasts, tiredness, poor sleep and mood changes, and the fall in both hormones before a period is linked with premenstrual symptoms. Prostaglandins released as the lining sheds add to period cramps. Mild changes are common, but severe monthly mood symptoms are worth a doctor visit, and our guide to PMS vs PMDD explains the difference.
What Can Cause Hormone Imbalances?
Conditions that can disrupt how hormones change during the menstrual cycle include: PCOS, thyroid disorders, high stress, significant weight changes, over-exercising, and perimenopause. According to Cleveland Clinic, any of these can throw off the normal rise and fall of FSH, LH, estrogen, or progesterone, leading to irregular or late periods, missed ovulation, or unpredictable cycles. Persistent changes are worth discussing with a doctor rather than assuming they’ll resolve on their own.
Help for Imbalanced Hormones and Irregular Periods
Irregular periods are often the first sign of a hormone problem. See a doctor if you have:
- No period for three months or more and you are not pregnant
- Cycles that are repeatedly shorter than 21 days or longer than 35 days
- Very heavy bleeding, bleeding between periods or severe pain
- Signs such as excess hair growth, acne or unexplained weight change alongside irregular periods
A doctor will usually ask about your cycle history and may check a pregnancy test and blood tests, such as FSH, LH, estradiol, progesterone, thyroid hormone (TSH) and prolactin. Some are timed to a day of your cycle, so ask when to book them. Treatment depends on the cause, for example treating a thyroid problem (thyroid and the menstrual cycle), managing PCOS, or addressing stress, weight or over-exercise. Avoid starting supplements or hormones on your own. Read more in our guide to menstrual cycle irregularities.
Hormonal Health and Health Insurance
Coverage differs by country, insurer and plan, so check yours before booking. It helps to ask whether hormone blood tests and pelvic ultrasounds are covered, whether you need a referral to a gynecologist or endocrinologist, and whether any approval is needed in advance. In public health systems such as the NHS, tests are usually arranged by your doctor when they are medically needed.
Bring a cycle log and a list of symptoms to your appointment. They help your doctor decide which tests are needed and can support a claim if your insurer asks why they were ordered.
Frequently Asked Questions
What hormones control the menstrual cycle?
What hormone is highest right before your period?
What triggers ovulation?
Why does progesterone rise after ovulation?
What happens to hormones if you don’t get pregnant?
Can hormone imbalances affect my cycle?
Can you feel your hormones changing during your cycle?
How quickly do hormones change during the menstrual cycle?
What day of your cycle are hormones the lowest?
What are reproductive hormones?
How many hormones are involved in the menstrual cycle?
Does health insurance cover hormone testing?


Sources & References
- Cleveland Clinic. Menstrual Cycle (Normal Menstruation): Overview & Phases. Overview of the four cycle phases (menstrual, follicular, ovulation, luteal) and the hormonal shifts that drive each one — the structural basis for this article. my.clevelandclinic.org
- Cleveland Clinic. Estrogen: Hormone, Function, Levels & Imbalances. Explains estrogen’s rise during the follicular phase and its role in triggering the LH surge — source for this article’s “How Estrogen and Progesterone Work Together” section. my.clevelandclinic.org
- Cleveland Clinic. Hormonal Imbalance: Causes, Symptoms & Treatment. Lists PCOS, thyroid disorders, high stress, significant weight changes, over-exercising, and perimenopause as common causes of disrupted FSH, LH, estrogen, or progesterone patterns — the basis for this article’s “What Can Cause Hormone Imbalances?” section. my.clevelandclinic.org
- American College of Obstetricians and Gynecologists (ACOG). Trying to Get Pregnant? Here’s When to Have Sex. Confirms the LH surge typically precedes egg release by roughly 24 to 36 hours, which is what ovulation predictor kits are designed to detect — supporting this article’s “LH Surge and Ovulation” section. acog.org