
Weight Changes and Menstrual Cycle What to Know
Both losing and gaining weight can throw off ovulation. Here is the hormonal pathway behind it, what the research shows, and the point where irregular cycles are worth a doctor’s visit.
Key Takeaways
- Weight changes and menstrual cycle problems are linked in both directions: losing weight and gaining weight can each disrupt ovulation.
- Low body fat lowers leptin, which weakens the brain signal that triggers ovulation. Excess body fat raises estrogen and insulin resistance.
- Energy availability matters more than the number on the scale.
- A cycle longer than 45 days, or no period for 3 months, needs evaluation.
- Cycles often recover once nutrition or the underlying cause is addressed.
If your periods started acting up around the same time your weight shifted, that is not a coincidence. Both losing weight and gaining weight can throw off ovulation, sometimes within a single cycle, and there is a real, well-studied hormonal pathway behind it.
This guide explains the actual mechanism, how weight loss and weight gain disrupt cycles differently, the clinical point where it is worth getting evaluated, and how long cycles typically take to settle.
Yes, body weight and your cycle are directly linked. Low body fat lowers leptin, which weakens the signal that triggers ovulation. Excess body fat raises estrogen and insulin resistance, which disrupts the same signal differently. Either direction can cause irregular, missed or delayed periods, and both are usually reversible once addressed.
Weight Changes and Menstrual Cycle: The Real Mechanism
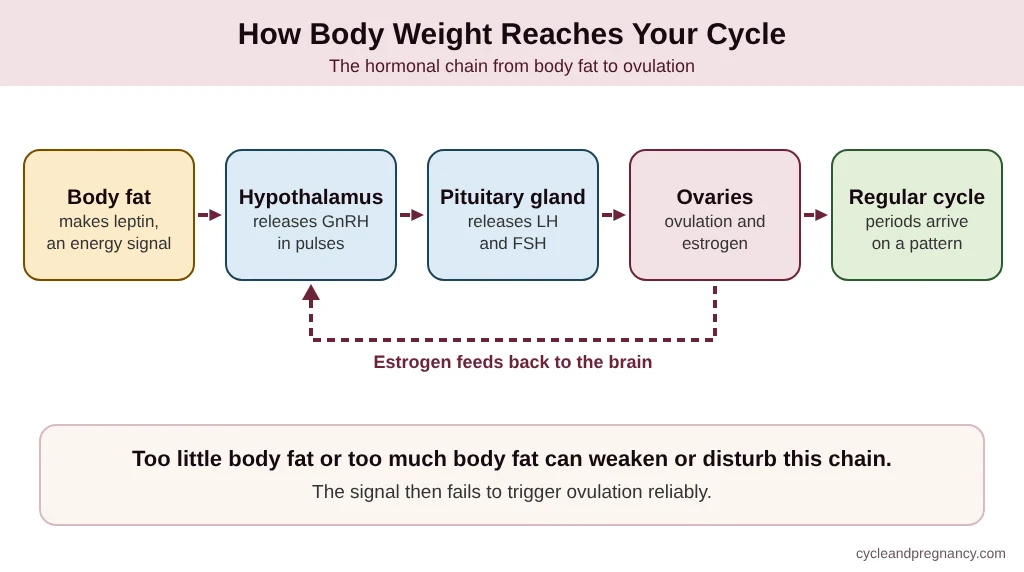
Body fat sends an energy signal to the brain. Too little or too much changes how well that signal triggers ovulation.
The HPO Axis
Your menstrual cycle is controlled by a signaling chain called the hypothalamic-pituitary-ovarian (HPO) axis. The hypothalamus releases GnRH in pulses, which tells the pituitary gland to release the LH and FSH that drive ovulation. Body fat plays a direct role in keeping that signal running.
Three Pathways
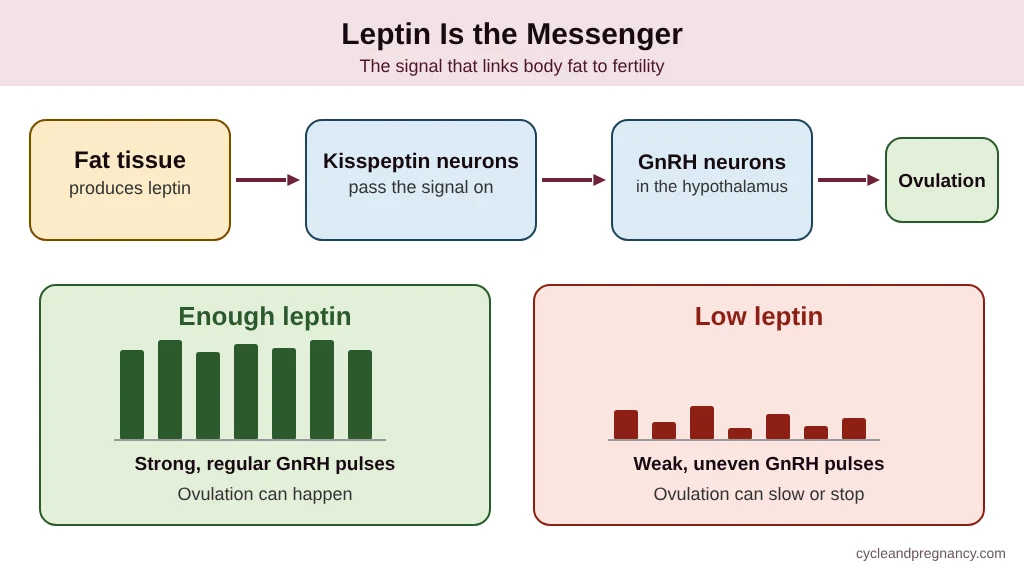
Leptin is the central hormone behind this disruption. It is produced by fat tissue and signals the hypothalamus about the body’s energy reserves. GnRH neurons do not have leptin receptors directly. Instead, leptin acts through intermediate neurons (involving kisspeptin) that connect to and help drive GnRH release. When leptin drops, as it does during significant weight loss or low energy availability, that pulsatile GnRH signal weakens, and ovulation can slow or stop.
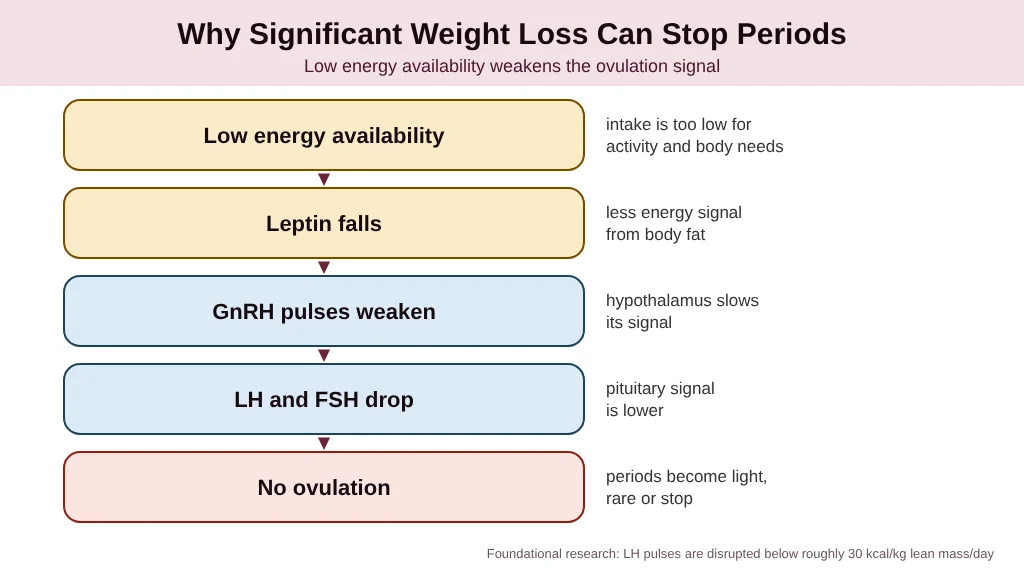
It is less about total pounds lost and more about energy availability: how much energy is left for the body’s basic functions after activity and calorie intake. Foundational research on exercising women found that LH pulsatility (the signal that drives ovulation) is disrupted once energy availability drops below roughly 30 kcal per kilogram of lean body mass per day, however the deficit arises. A large, sustained deficit lowers leptin, which weakens the GnRH signal described above. This is the same mechanism behind exercise-related amenorrhea in athletes with very high training loads and insufficient fueling.
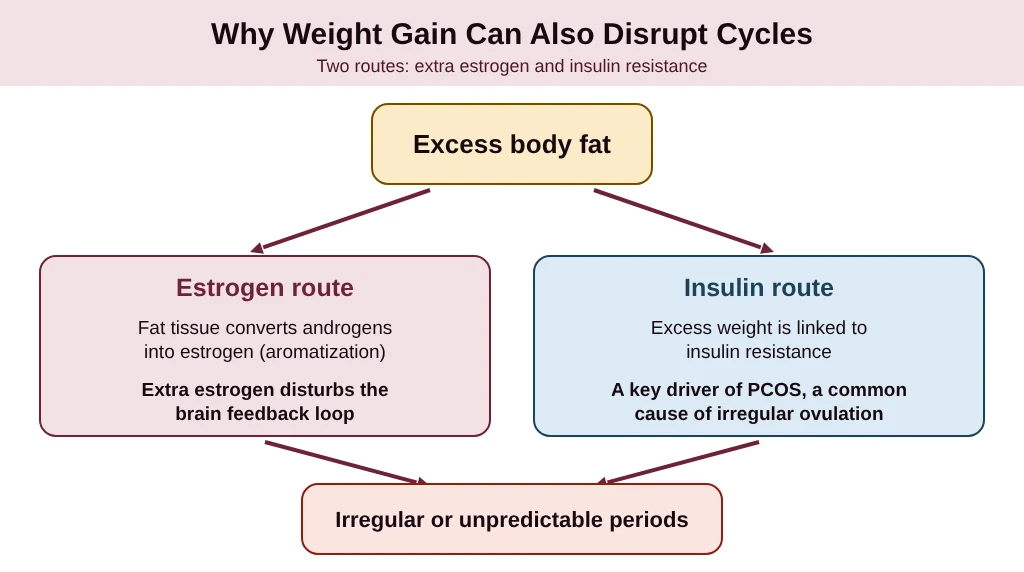
Fat tissue does not only produce leptin. It also converts androgens into estrogen through a process called aromatization. With significant excess body fat, this can push estrogen levels up in a way that disrupts the normal feedback loop the HPO axis relies on. Excess weight is also closely tied to insulin resistance, which is a key driver of PCOS, one of the most common causes of irregular ovulation.
Does BMI Affect Your Menstrual Cycle?
BMI well below or well above the typical range is linked to more irregular or missing periods, but it is a screening tool, not a verdict.
BMI Ranges and Cycle Risk
BMI is one of the most searched terms alongside period irregularity, and it is a reasonable starting point for understanding risk. Both a BMI well below and well above the typical range are associated with higher rates of irregular or absent periods, largely through the same leptin and estrogen pathways described above.
| BMI range | Cycle-related risk |
|---|---|
| Under 18.5 (underweight) | Higher risk of low leptin, anovulation and amenorrhea |
| 18.5 to 24.9 (typical range) | Lowest population-level risk of weight-related cycle disruption |
| 25 to 29.9 (overweight) | Increased risk of irregular ovulation, especially with PCOS |
| 30 and above (obesity) | Higher rates of anovulation, heavier or unpredictable bleeding |
BMI does not account for muscle mass, body composition or individual variation, so two people with the same BMI can have very different cycles. It is a population-level signal. What matters more for your own cycle is energy availability, body fat percentage and any underlying condition like PCOS or FHA.
Is Weight Gain Around Your Period Normal?
A temporary rise of roughly 1 to 2 kg (2 to 5 lb) around your period is common and is mostly water, not fat.
How Much Is Typical
Many people notice the scale creeping up in the days before bleeding starts. Small swings of about 1 to 2 kg (2 to 5 lb) are commonly reported and usually ease within a few days of the period beginning. A gain that keeps climbing, or does not settle by the end of your period, points to something other than your cycle.
Why the Scale Moves Before and After
| Timing | What is happening | Usual effect |
|---|---|---|
| Late luteal phase (before the period) | Rising and then falling estrogen and progesterone make the body hold on to sodium and water | Bloating and a temporary rise on the scale |
| Days before the period | Cravings and a larger appetite are common as hormones shift | Slightly higher food intake and gut gas |
| First days of the period | Prostaglandins can slow or speed digestion, and fluid starts to shift out | Bloating that gradually eases |
| After the period | Water balance returns to your usual level | Weight drifts back to baseline |
Because this is mainly fluid, it is not the same as gaining body fat. Weigh yourself at the same point in each cycle if you want a fair comparison. For the digestive side of it, see our guide to Period Bloating Causes and Relief.
How Weight Loss vs. Weight Gain Affect Periods Differently
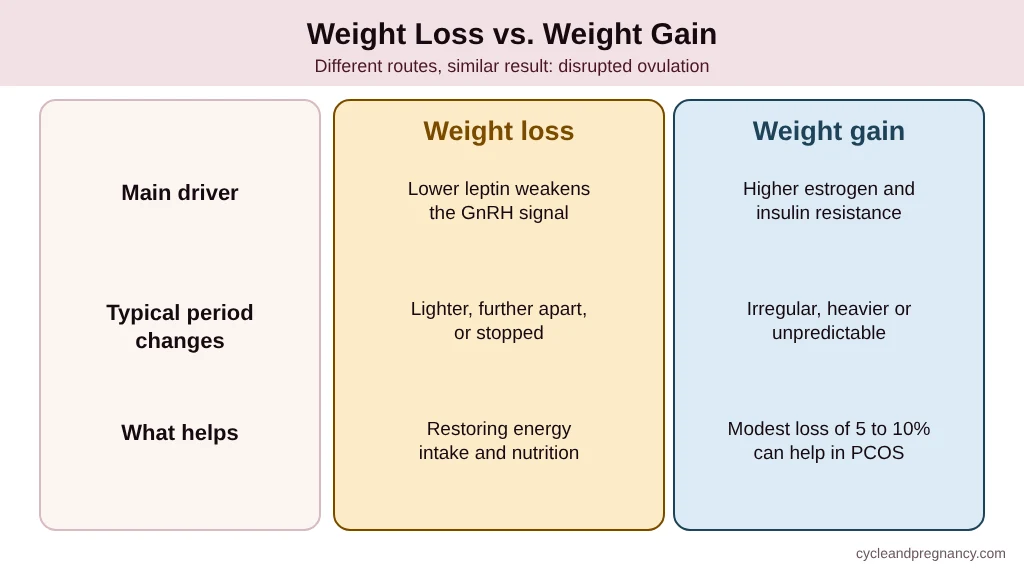
Weight loss weakens the ovulation signal through low leptin. Weight gain disturbs it through extra estrogen and insulin resistance.
Side by Side
| Feature | Weight loss or low energy availability | Weight gain or excess body fat |
|---|---|---|
| Main driver | Lower leptin weakens the GnRH signal | Higher estrogen from aromatization and insulin resistance |
| Typical period changes | Lighter, further apart, or stopped | Irregular, heavier or unpredictable |
| Common link | Rapid loss, very low intake, high exercise volume; functional hypothalamic amenorrhea | PCOS and insulin resistance |
| What helps | Restoring energy intake and nutrition | Modest weight loss of 5 to 10% can improve ovulation in women with PCOS and obesity |
A 2026 randomized trial found that ovulatory recovery improves progressively as total weight loss increases. If PCOS is part of your picture either way, our guide to PCOS and Ovulation covers symptoms and diagnosis in depth.
Functional Hypothalamic Amenorrhea: When Weight Loss Stops Periods Entirely
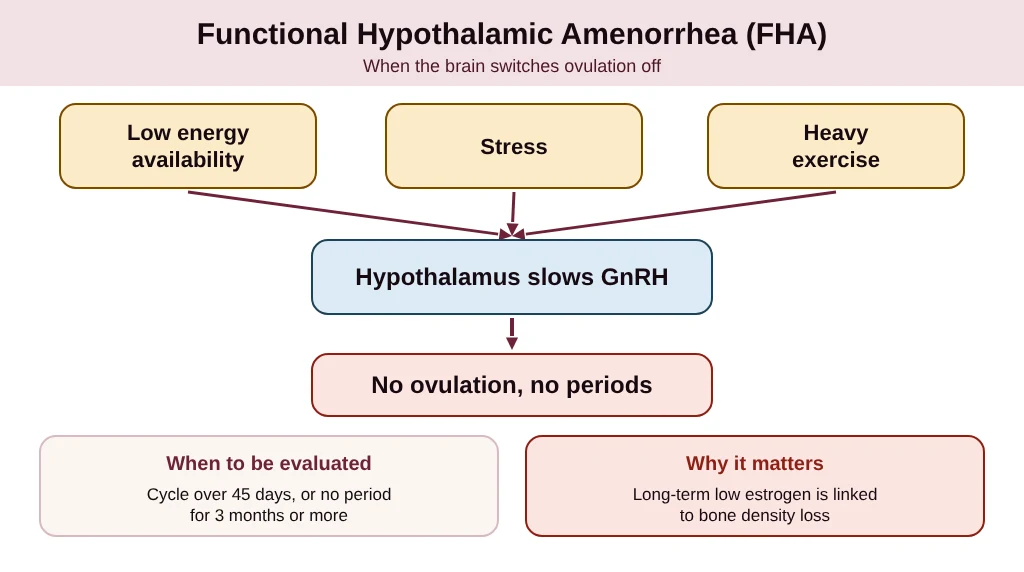
When low energy availability, stress or heavy exercise switch off ovulation, the diagnosis is functional hypothalamic amenorrhea (FHA).
What FHA Means
This is the most extreme end of the pattern. When periods stop altogether due to low energy availability, stress or excessive exercise (alone or combined), the clinical name is functional hypothalamic amenorrhea (FHA). It is recognized as a diagnosis of exclusion in the Endocrine Society’s clinical practice guideline, meaning other causes are ruled out first.
When It Is Flagged
Cycle interval over 45 days. The guideline’s suggested threshold for evaluation.
Amenorrhea for 3 months or more. Also flagged for evaluation, and pregnancy should always be ruled out first.
Often paired with low body weight, low body fat, very restrictive eating, or high training volume without matching fuel intake.
Why It Matters
FHA is not just an inconvenience. Prolonged low estrogen from this condition is linked to bone density loss, so it is worth taking seriously rather than waiting it out. ACOG’s guidance on amenorrhea also notes that most people benefit from a combination of adequate nutrition, exercise moderation and stress reduction. For related causes see Exercise and the Menstrual Cycle and How Stress Affects Your Period.
How Long Until Periods Become Regular Again?
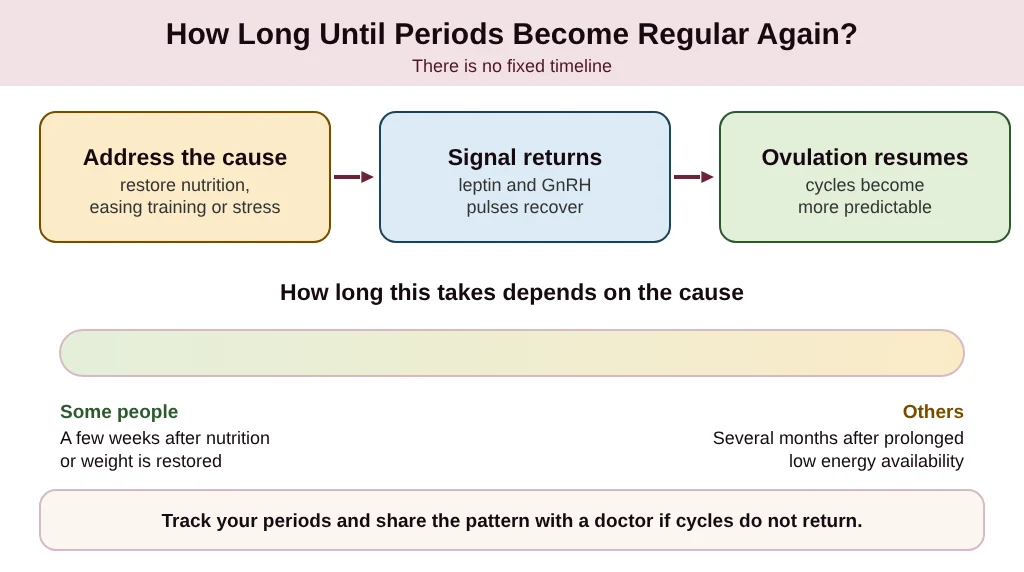
From a few weeks to several months, depending on the cause and how it is addressed.
No Fixed Timeline
Recovery time for weight changes and menstrual cycle disruption depends heavily on what caused the change and how it is addressed. Some people see cycles normalize within a few weeks of restoring adequate nutrition or stabilizing weight. For others, especially after prolonged low energy availability, it can take several months.
Track While You Wait
Logging your periods with a Period Calculator gives you, and a doctor if needed, real data about how things are trending. If the weight and cycle shifts happened together, that pattern itself is worth mentioning at your next appointment, even if nothing else seems wrong.
When to See a Doctor
Get checked for cycles over 45 days, 3 months without a period, new symptoms like excess hair growth, or rapid weight loss with missed periods.
Signs Worth Acting On
Most weight changes and menstrual cycle disruption is common and settles on its own, but a few signs call for action:
Cycle length consistently longer than 45 days · No period for 3 months or more (and pregnancy is ruled out) · New symptoms like excess hair growth, acne or persistent fatigue alongside irregular cycles · Significant, rapid weight loss alongside missed periods · Heavy or unpredictable bleeding alongside weight changes.
Related Causes to Rule Out
If bleeding is heavy or unpredictable, see our Heavy Periods Guide. A late period can also have other causes, covered in Why Is My Period Late, and thyroid problems are another common one: see Thyroid and Menstrual Cycle. If you are postpartum, hormonal shifts follow a related but distinct pattern, covered in Periods While Breastfeeding.
Frequently Asked Questions
12 questions answeredCan losing weight affect your period?
Can gaining weight affect your period?
How much weight loss does it take to stop your period?
How long does it take for periods to become regular again after a weight change?
Can weight gain help irregular periods caused by low body weight?
What is functional hypothalamic amenorrhea?
When should I see a doctor about weight-related period changes?
Does a low BMI affect your period?
Can obesity cause irregular periods?
How much weight gain is normal during a period?
Can crash dieting delay my period?
Can stress or heavy exercise stop my period too?


Sources & References
- Gordon CM, Ackerman KE, Berga SL, et al. Functional Hypothalamic Amenorrhea: An Endocrine Society Clinical Practice Guideline. J Clin Endocrinol Metab. 2017;102(5):1413–1439. doi:10.1210/jc.2017-00131. PMID: 28368518. PubMed · Full text (Oxford Academic)
- Loucks AB, Thuma JR. Luteinizing Hormone Pulsatility Is Disrupted at a Threshold of Energy Availability in Regularly Menstruating Women. J Clin Endocrinol Metab. 2003;88(1):297–311. doi:10.1210/jc.2002-020369. PMID: 12519869. PubMed
- Samarasinghe SNS, Abbara A, Ortega PM, et al. Ovulatory Recovery Following Weight Loss in Women With Polycystic Ovary Syndrome and Obesity: A Post Hoc Analysis of the BAMBINI Randomised Controlled Trial. Human Reproduction. 2026;41(5):809–817. doi:10.1093/humrep/deag037. PMID: 41808368. PubMed · Full text (Oxford Academic)
- Chen X, et al. The Effects of Weight Loss-Related Amenorrhea on Women’s Health and the Therapeutic Approaches: A Narrative Review. Annals of Translational Medicine. 2023. Full text
- Al-Safi ZA, Polotsky AJ, et al. Variation of Leptin During the Menstrual Cycle and Its Relation to the Hypothalamic-Pituitary-Gonadal Axis. International Journal of Women’s Health. Dove Medical Press. Full text
- American College of Obstetricians and Gynecologists (ACOG). Amenorrhea: Absence of Periods. acog.org
- Cleveland Clinic. Yes, Weight Loss Can Impact Your Menstrual Cycle. clevelandclinic.org
- Mayo Clinic. Premenstrual Syndrome (PMS) — Diagnosis and Treatment. mayoclinic.org
- Clue (Biowink GmbH). How Weight & BMI Can Affect Your Period. helloclue.com